


Donate
Support Care
Articles & News
Field stories
Glossary
Field guides

Health & Medical Program
Primary Medical Care
First-line assessment, treatment, prevention and referral for families living hours from a clinic and beyond reliable transport.
- Active since December 2022
- 27 Kawan Sehat agents
- 700 to 1,000 patients each month
Care starts where the road ends
In East Sumba, distance changes the course of illness. A fever, infected wound or dehydrated child may worsen for hours before transport is possible. Trained Kawan Sehat agents begin assessment, safe first-line care and referral inside the village.
The programme
A local health system built for distance
Here, distance is a clinical risk. A fever can become severe, a wound can progress to sepsis, and a pregnancy complication can turn critical before a family reaches formal care.
Primary Medical Care places trained Kawan Sehat health agents inside their own communities. They are not substitutes for doctors. They are the first safe point of contact: close enough to act early, trained enough to recognise danger and connected to medical supervision when a case exceeds local capacity.
Care is provided without charge at the point of service. Medicines, dressings, diagnostic supplies, education tools and reporting systems are carried into areas where routine health infrastructure is absent or difficult to reach.
Women and men working inside their own villages, with structured training and support.
Assessment, treatment, education, follow-up and referral carried out close to home.
Medicines, dressings and basic diagnostic supplies are checked and replenished regularly.
The programme began in December 2022 and continues as a permanent field operation.
From first contact to follow-up
How care reaches a patient
Every consultation must connect observation to a safe decision. Symptoms, vital signs, treatment, danger signs, referral and follow-up are documented so care does not end when the agent leaves the house.
First contact
A nearby Kawan Sehat agent listens, examines and records the patient’s symptoms and history.
Assessment
Vital signs, danger signs and the limits of community treatment guide the next decision.
Care or referral
Safe basic care is provided locally. Severe or uncertain cases are referred without delay.
Documentation
The Kawan Sehat app and field records support case review, follow-up and disease surveillance.
Follow-up
The agent returns, checks progress, reinforces prevention and contacts the medical team when needed.
Clinical boundaries matter
Care close to home, referral when risk rises
The most important clinical skill is knowing the limit of local care. Agents work within defined protocols, treat what is safe, and refer immediately when symptoms, vital signs or uncertainty indicate higher risk.
What agents can do
- Assess symptoms, temperature and available vital signs
- Clean and dress superficial, uncomplicated wounds
- Provide protocol-approved first-line medicines and oral rehydration
- Support uncomplicated fever, respiratory, skin and digestive complaints
- Monitor older people, children and patients with chronic conditions
- Teach hygiene, nutrition, malaria, tuberculosis, HIV and infection prevention
When agents refer
- Breathing difficulty, altered consciousness, shock or severe dehydration
- Suspected sepsis, severe infection or rapidly worsening illness
- Major trauma, deep wounds, burns or suspected fracture
- Pregnancy complications or danger signs in a mother or newborn
- Possible tuberculosis, leprosy, HIV or another condition requiring medical testing
- Any presentation that is uncertain or beyond available skills, protocols or supplies

Medicines matter, but safe use depends on training, documentation, clean equipment, supervision and regular restocking.
The system behind each visit
Tools that make continuity possible
A bag of medicines alone is not a health system. Each visit depends on trained judgement, a defined medicine list, clean dressings, usable records, follow-up and access to medical supervision. Standardising these foundations reduces unsafe improvisation and makes every case reviewable.
150-page manual
Fourteen training modules covering first-line care, prevention, danger signs and safe practice.
Kawan Sehat app
Offline and online case documentation designed for villages with weak connectivity.
Medical kits
Medicines, dressings, basic diagnostics and prevention materials adapted to field conditions.
Medical supervision
Training, case review, field visits, referral support and regular supply control.
What changes in practice
Earlier care changes the course of illness
Shorter delay to first care
A child, older person or injured worker can be assessed the same day instead of waiting for money, a vehicle or a passable road.
Safer treatment decisions
Defined protocols, supervised medicine lists and case review reduce unsafe improvisation and avoidable self-medication.
Clearer referral
Referral begins with recorded symptoms, vital signs, treatment already given and the danger signs observed.
Prevention inside daily life
Malaria, tuberculosis, HIV, wound infection, hygiene and nutrition are discussed at home, in schools and during care, in language people understand.
Clinical manualPrimary Medical Care field manualOpen the 150-page manual used to structure assessment, treatment, prevention, follow-up and referral.
PeopleMeet the Kawan Sehat agentsUnderstand who provides care and how community knowledge becomes clinical action.
Field toolsDigital tools for rural careSee how field applications support patient records, follow-up, evidence and safer decisions.
ResearchSumba Sepsis Study 2026Explore evidence on infection, delayed care and household risk across 1,001 families.
Live field recordField Notes from Eastern IndonesiaFollow short, dated updates on care, prevention, research, logistics and the realities teams meet.
Field guide & glossaryHealth and care, explainedExplore clinical terms and practical field guides grounded in Fair Future’s work in remote communities.
Medical referenceWHO primary health careRead the international framework connecting treatment, prevention and community participation.
Live from the field
Medical Field Notes, as the work happens
Two recent signals from care, research and prevention in East Sumba. These notes refresh from the Field Notes archive when a new medically relevant update is published.
Directly from the field
Latest Primary Medical Care reports
These field reports document the care actually delivered: clinical problems encountered, prevention work, referrals, supply constraints and the decisions our teams make in remote villages.
Work in preparation includes community care days connecting consultations with practical prevention and support for the next medical care day in Bidi Hunga.

PMC program evaluation in Mbatapuhu
Non-professionals who give medical care and medicine to people, sick children, and injured. They do so through a unique and innovative medical care program. Because here, there are no doctors, no health centre, or else too far away. No one has a vehicle, and the roads that lead to these villages are often impassable.

PMC – Teachers receive their training certificate
In Kabanda village, East Sumba, three teachers, participants in the Primary Health Care Program, receive a vocational training certificate for the 1st time.

Evaluation of 8 Kawan Sehat agents, in Mbinudita
In the village where it all started for us: The #rebuildmbinudita program is the construction of a school, and the construction of a drinking water network for more than 2700 people, 60% of whom are children under 12 years old . It is really the (re)construction of an entire village or learning to live healthier, healthier all together, within…

PMC program pre-assessment in Mbinudita
Fair Future teams examine and investigate more than two hundred cases of various illnesses or injuries treated under the primary medical care program by health workers. We also take stock of what will happen next week to accurately assess the supply of new equipment, drugs and medical devices.

Primary medical care dedicated to children
Children in remote East Sumba learn simple daily habits that can reduce illness and injury where access to professional healthcare is limited.

Learn how to provide Primary Medical Care
Teachers and community health workers learn practical first aid and primary medical care for villages where professional healthcare is hard to reach.

Learning how to live healthier in rural areas
Thanks to the Fair Future & Kawan Baik teams on site and the various publications that our two foundations have produced for them, we share a few hours in each group of houses, in each village where Fair Future and Kawan Baik have carried out one or more projects related to access to drinking water and to toilets and other sanitary facilities.

On-site Primary Medical Care Program Assessment
This primary medical care program in ultra-rural areas, which we initiated and started last year, is extraordinary, it saves lives. Since December 2022, the participants in the primary medical care program – who are the village teachers – have been providing first aid to children and villagers. They treat wounds, diseases, malaria, dengue fever.

Teachers provide primary medical care
The magic of this “Primary Medica Care” program? It’s just that it’s unique in the world and it works. The first batch of sixty teachers who have followed the training in primary medical care in rural areas, tell us about their “exploits” and their work as rescuers. They take confidence in themselves it is the most important, and we note it.

Primary medical care training for 60 teachers
Whether a minor skin injury or a severe life-threatening injury, all types of damage should be treated with first aid on the spot without delay, as it may save a life or a limb. Teachers in the poorest and most rural areas learn this with Fair Future’s medical teams.

Kawan Sehat, the full book for a healthier life
The Foundation has created an illustrated book for the young in the ultra-rural areas of eastern Indonesia. Where knowing how to read and write is not shared. It will serve as a reference book and gather most of the information on a better lifestyle, the tips and tricks that are “normal” but that most don’t know here.
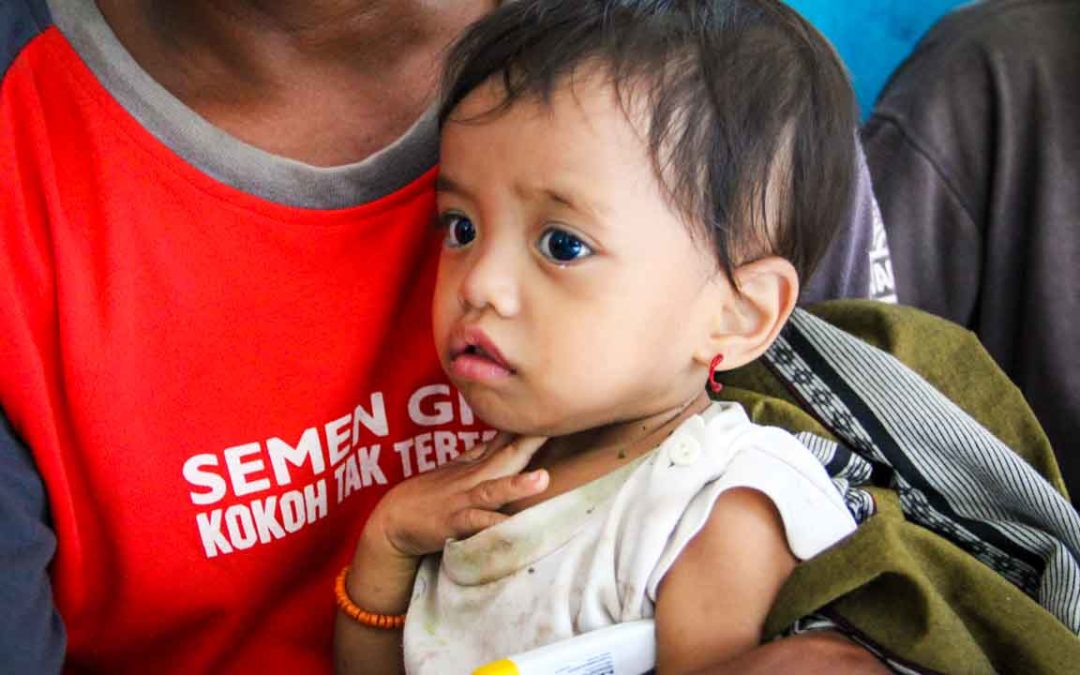
Primary medical care for kids in rural areas
The inhabitants of rural villages do not have access to primary care, and most medical centres are often several hours away on foot. The harshness of life here means we often get hurt, but nothing is available to treat ourselves—no doctor, knowledge, medical equipment and, of course, no antiseptic or medicine.
Accountability
Care must remain measurable, reviewable and transparent
A programme caring for 700 to 1,000 patients each month must show more than activity. We document medicines used, care delivered, referrals, prevention work, field limits and how resources are engaged. What works is strengthened. What fails is corrected and reported.
